


Advanced Complete & Partial Dentures in Delhi (Dwarka):
The Bio-Functional (BPS) Denture & Implant Architecture
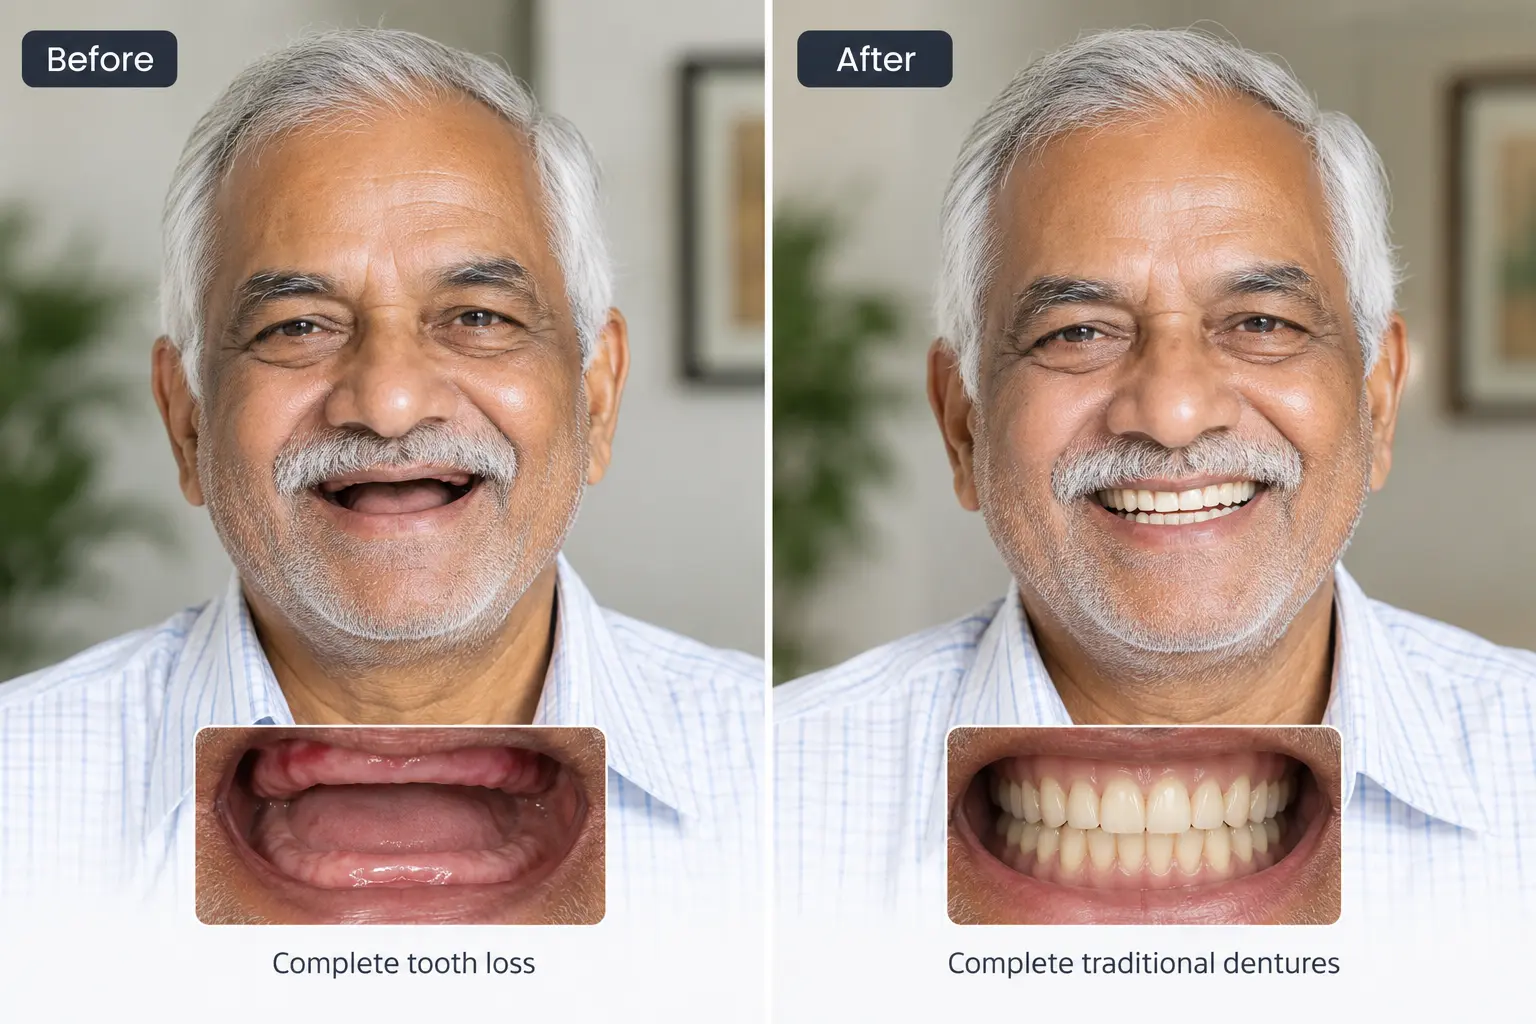
Tooth loss alters more than appearance—it disrupts masticatory biomechanics, triggers accelerated bone resorption, and collapses facial balance. Led by Dr. Yogesh Rao (MDS, Prosthodontist & Implantologist), Oraa Care Smile Dental Clinic replaces traditional trial-and-error techniques with 3D volumetric diagnostics, precision gnathometric tracing, and biocompatible material engineering.
The Anatomy of Modern Dentures: Categories & Clinical Indications
Denture Restoration Spectrum
In specialist prosthodontics, a denture is not treated as a temporary cosmetic cover, but as an engineered medical appliance designed to protect residual alveolar ridges, restore balanced temporomandibular joint (TMJ) loads, and rebuild facial vertical height. Prosthetic options are categorized based on individual dental and bone anatomy:
Complete Dentures
Engineered for total tooth loss (full-arch edentulism). Retained via peripheral mucosal suction, surface tension, and physiological muscular seating across the upper or lower ridge.
Partial Dentures
Indicated when natural abutment teeth remain. Designed with medical-grade cast cobalt-chromium frameworks or high-flexibility nylon polymers (Valplast) to redistribute occlusal forces.
BPS® Dentures
The Biofunctional Prosthetic System. Employs dynamic muscular impressions, Gnathometer tracing of jaw joint axes, and continuous pressure-injected micro-shrinkage curing.
Fixed Implant Dentures
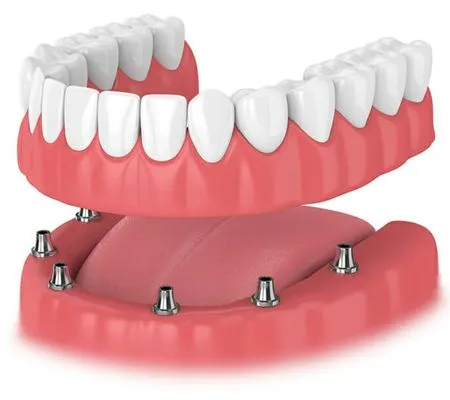
Implant-anchored hybrid bridges permanently attached to basal bone, providing complete biting recovery without palatal coverage or daily adhesives.
Diagnostic Assessment: When Removable Dentures are Mandatory
Biological Indications
Partial dentures are specifically indicated when conservative fixed crown-and-bridge options are contraindicated or biomechanically unsound:
- Free-End Saddle Scenarios (Missing Posterior Molars): When terminal back molars are absent, there is no posterior anchor tooth to support a fixed bridge. A precision partial restores chewing without requiring complex bone grafting.
- Long-Span Edentulous Gaps: Spanning three or more continuous missing teeth with a traditional tooth-supported bridge exerts dangerous leverage on natural abutments. Precision partials distribute bite forces evenly across tissue and teeth.
- Periodontally Compromised Secondary Dentition: Where remaining natural teeth present reduced alveolar bone height, a cast-metal partial denture stabilizes adjacent teeth as a cross-arch splint while replacing missing units.
- Staged Transitional Rehabilitation: Serving as an aesthetic, non-invasive provisional appliance while post-extraction sites heal prior to definitive implant placement.
Why Removable Systems Remain the Only Viable Alternative for Specific Cases
While implant restorations offer substantial benefits, clinical conditions often make high-precision removable prosthetics the safest choice:
- Severe Skeletal Ridge Resorption: Patients experiencing progressive vertical and horizontal bone loss where extensive nerve-repositioning, sinus floor lifts, or zygomatic implants present elevated surgical risks.
- Systemic Medical Contraindications: Uncontrolled metabolic conditions (Type 2 diabetes), systemic immunosuppression, active radiation therapy to the head/neck, or intravenous bisphosphonate therapy (risk of Medication-Related Osteonecrosis of the Jaw – MRONJ).
- Compromised Manual Dexterity: Neuromuscular limitations, arthritis, or stroke sequelae that prevent the detailed interproximal hygiene required beneath fixed implant hybrid bridges. Removable dentures allow thorough cleaning by the patient or their caregivers.
- Financial Feasibility: Precision removable dentures engineered to correct bite relationships provide predictable oral rehabilitation within controlled budgets.
The Clinical Hazards of Substandard Commercial Dentures
Toxic Monomer Risks
Low-cost, commercial-grade dentures compromise foundational biological health. Selecting budget-driven dental appliances fabricated in non-standardized dental laboratories carries documented clinical risks:
Toxic Residual Monomer Leaching
Economical cold-cured or poorly processed acrylic resins undergo incomplete polymerization, releasing residual methyl methacrylate monomer. This chemical leaching causes chronic mucosal erythema, oral contact stomatitis, burning mouth symptoms, and allergic hypersensitivity reactions across oral tissues.
Rapid Misfit & Accelerated Bone Loss
Cheap acrylic undergoes unmanaged volumetric curing shrinkage of 3% to 6%, resulting in a poorly adapting base plate. The irregular contact points apply uneven localized pressure spikes directly against fragile alveolar ridges, accelerating irreversible underlying bone resorption within months of delivery.
Microbial Harboring via High Porosity
Substandard processing leaves microscopic voids and porosities across the denture base. These internal spaces harbor complex fungal and bacterial colonies—predominantly Candida albicans—which trigger chronic denture-induced stomatitis, persistent halitosis, and recurrent systemic aspirational infections.
Biofunctional Prosthetic System (BPS) Dentures
BPS Engineering
The Biofunctional Prosthetic System (BPS), certified by Ivoclar Vivadent, resolves the primary pain points of standard dentures: instability during speech, localized friction ulcers, and unnatural dental profiles.
Unlike conventional dentures molded from static impression trays, BPS protocols record the continuous functional movements of surrounding cheek, lip, and tongue musculature. By utilizing a Gnathometer Gothic Arch Tracer, Dr. Yogesh Rao determines the exact centric relationship of the temporomandibular joints, matching the mechanical profile of the replacement teeth directly to your natural jaw movements.
 BPS Multi-Layered Biomimetic Setup with Anatomical Gingival Contouring
Fixed Implant-Supported Dentures: Permanent Full-Arch Rehabilitation
Fixed Implant Protocols
Fixed implant dentures replace removable plates with permanently anchored full-arch dental frameworks. Guided by 3D Cone Beam Computed Tomography (CBCT), titanium or zirconia implants are placed with sub-millimeter precision. These implants osseointegrate directly into the bone, supporting permanent, natural-feeling teeth that eliminate speech impediments, eliminate slippage, and preserve facial contours.


Clinical Comparison Matrices: Evidence-Based Tradeoffs
Evaluating functional differences, biological longevity, and clinical maintenance.
1. Fixed Implant Dentures vs. Traditional Removable Dentures
| Parameter | Fixed Implant Dentures (All-on-4 / All-on-6) | Traditional Complete Dentures |
|---|---|---|
| Fixation Mechanism | Rigid biological osseointegration into bone | Mucosal suction and peripheral ridge seal |
| Masticatory Efficiency | 85% – 95% of natural bite force capacity | 20% – 25%; restricted to softer diets |
| Bone Preservation | Maintains bone via direct micro-strain stimulation | Accelerates bone ridge loss from external friction |
| Palatal Coverage | Open horseshoe framework (Taste/temperature preserved) | Full acrylic coverage across the hard palate |
| Clinical Longevity | Long-term permanent foundation (20+ years) | Requires relining every 2 years; replacement in 5–7 yrs |
2. BPS Precision Dentures vs. Traditional Standard Dentures
| Criteria | BPS (Biofunctional Prosthetic System) | Standard Traditional Denture |
|---|---|---|
| Impression Protocol | Dynamic functional border molding with active muscles | Static mucostatic tray impressions |
| Occlusal Recording | Mathematical Gnathometer intraoral needle-tracing | Visual wax bite rim alignment |
| Polymerization Method | SR Ivocap continuous pressure injection (Zero shrinkage) | Manual boil/cold-pack acrylic curing (2–4% shrinkage) |
| Tooth Durability | Cross-linked nanohybrid composite teeth (Anti-wear) | Conventional acrylic teeth prone to rapid wear |
| Tissue Irritation Risk | Extremely minimal due to uniform base fit | High incidence of recurring sore spots & pressure ulcers |
Facial Biomechanics & Biological Tissue Health
Facial Dimension Loss
Reversing Skeletal Facial Collapse
When natural teeth are missing or worn down, the anatomical distance between the tip of the nose and the chin shortens—a condition termed loss of Vertical Dimension of Occlusion (VDO). The lower jaw rotates unnaturally upward, creating thin, inverted lips, deep nasolabial creases, and premature facial aging. By calculating your anatomical joint trajectory, Dr. Yogesh Rao rebuilds original bite height, restoring youthful facial support.
Denture Stomatitis & Candidiasis Prevention
Ill-fitting dentures irritate delicate palatal mucosa, while porous, low-grade resins harbor Candida albicans biofilm. This results in denture-related stomatitis—a chronic, burning infection that leads to tissue hyperplasia. Our clinical team pairs medical-grade non-porous resins with routine tissue checks, preventing oral fungal colonization before it develops.
The 30-Day Neuromuscular Adaptation Roadmap
Salivary flow temporarily increases as the brain registers the appliance. Mild muscle tightness occurs around the lips and tongue as tissue seats against the polished borders.
Practice reading aloud to adapt to challenging “S” and “Th” sounds. Consume soft foods cut into small bites, chewing evenly on both sides to balance forces across the ridge.
The tongue and facial muscles naturally stabilize the base plate. Mastication becomes instinctive, soft tissues adapt to balanced loads, and confidence is fully restored.